

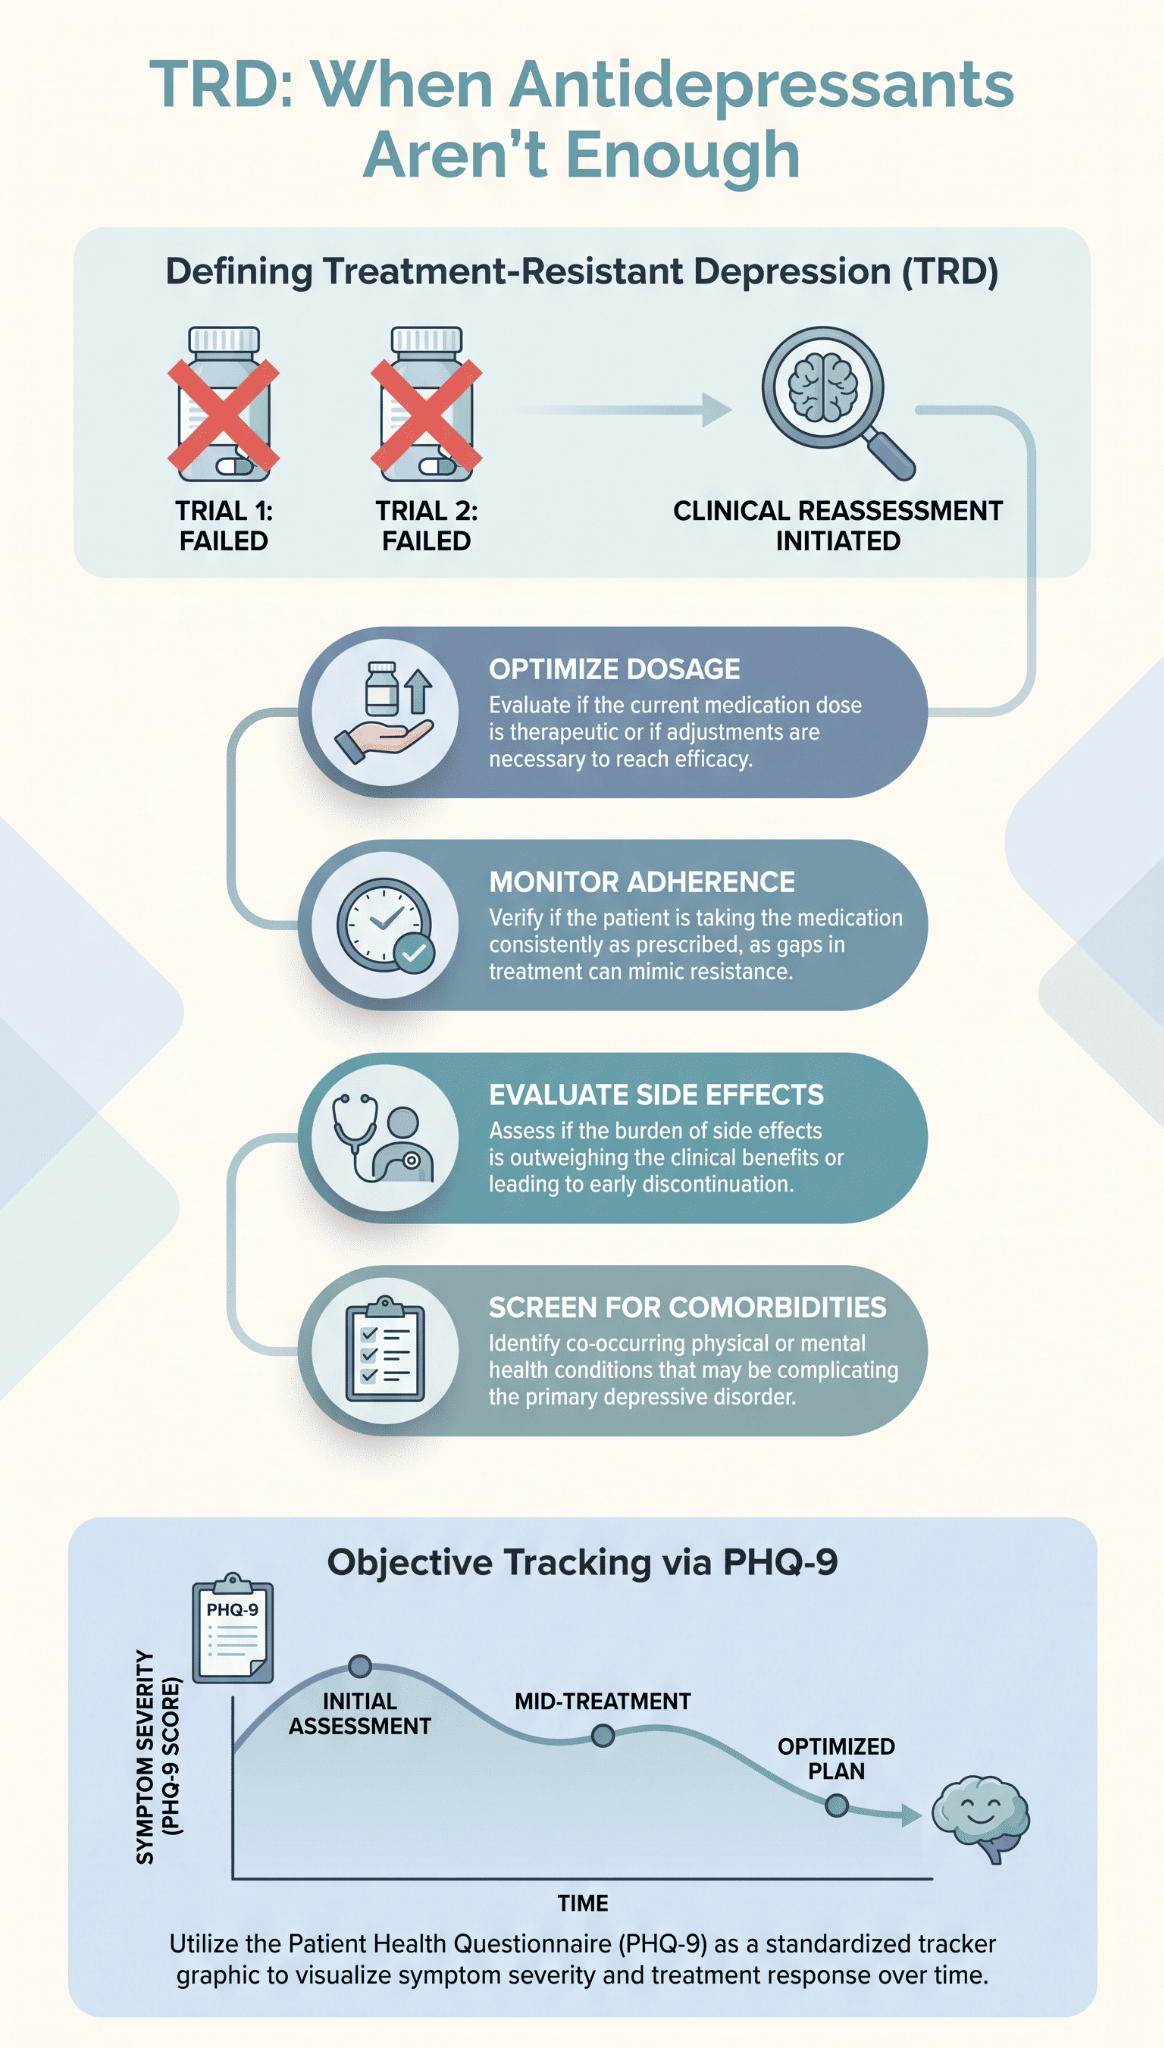
When depression persists after two adequate antidepressant trials, it’s often considered treatment-resistant depression (TRD). At this point, simply repeating the same failed approach is not an option; a deeper investigation is required. Clinicians may reassess the diagnosis, review past treatments, and consider other options based on the person’s symptoms and treatment history. Research suggests that at least 30% of people with depression meet a commonly used definition of treatment resistance.
Keep reading to learn what treatment-resistant depression means and what options may come next with Fit Mind Therapeutics.
Key Takeaways
- Two inadequate antidepressant trials may indicate treatment resistance.
- Review treatment history, adherence, diagnosis, and other conditions.
- Options include medication changes, therapy, TMS, ECT, or esketamine.
What Is Treatment-Resistant Depression?
Treatment-resistant depression occurs when you try at least two different antidepressants without experiencing sufficient relief. Each trial must involve the correct therapeutic dose taken consistently for an adequate duration. Clinicians carefully review your full medication history before confirming this diagnosis.
As noted by Mayo Clinic
“If you’ve been treated for depression but your symptoms haven’t improved, you may have treatment-resistant depression. Taking an antidepressant or going to psychological counseling (psychotherapy) eases depression symptoms for most people. But with treatment-resistant depression, standard treatments aren’t enough.” – Mayo Clinic
In my practice, I’ve found that definitions of ‘long enough’ and ‘improvement’ can vary among doctors. That’s why I avoid labeling someone as treatment-resistant until we’ve had an in-depth conversation about their specific experience with each medication.
Here’s the thing. A medication not working doesn’t mean it was useless. Before jumping to that conclusion, your doctor will usually check a few things first. Was the dose high enough? Did you take it consistently? Did you give it time? Did side effects force you to quit early?
And this is not the same as “difficult to treat depression.” They sound similar. They’re not identical. Difficult to treat depression just means symptoms are sticking around despite trying several approaches. No official failure count required.
So what does a review actually involve? Usually this:
- Which antidepressants you’ve tried, at what doses, for how long
- Whether you stuck with them, and how your body handled it
- Changes in your symptoms and daily functioning
- Other health conditions, mental or physical
- What you actually want out of treatment
Getting this label right matters. It shapes what your doctor considers next. If TMS becomes one of those options, your treatment history and previous response to depression treatment can also help determine whether you may be a candidate for NeuroStar TMS therapy in Jacksonville. A 2023 review in the Journal of Clinical Medicine noted that no single definition has caught on universally. That’s part of why estimates of how common this is vary so much.
How Is It Different From Difficult-to-Treat Depression?
The distinction between these two terms comes down to scope. Treatment-Resistant Depression (TRD) is a specific diagnostic threshold, while Difficult-to-Treat Depression (DTD) looks to the broader, real-world reality of living with ongoing symptoms.
Key Differences Breakdown
- Treatment-Resistant Depression (TRD): Defined strictly as depression that fails to respond adequately to at least two different antidepressant trials of adequate dose and duration.
- Difficult-to-Treat Depression (DTD): A broader concept that considers non-pharmacological factors, like ongoing life stress, co-occurring medical conditions, or partial response to therapy, rather than just medication failures.
Depression rarely fits into a tidy box. Plenty of people feel a little better on medication, but they still deal with poor sleep, low motivation, and trouble focusing. The improvement is real; it’s just not complete.
Doctors call that partial remission. It means symptoms eased, but didn’t fully go away. That calls for a different kind of conversation, not starting from zero. Your doctor will likely focus on what’s left, how much it’s getting in the way, and whether exploring TMS therapy in Ponte Vedra, FL could help close that gap with a qualified clinician.
How Common Is Treatment-Resistant Depression?
There’s no single agreed-upon number, but research suggests that roughly three out of every ten people with depression don’t improve after two real attempts at treatment.
What the Data Shows:
- 2023 Research Review: Indicates that about 30% of patients experience treatment resistance after two standard therapeutic trials.
Research from National Institutes of Health shows
“Depression is common among older adults, and treatment with standard antidepressants doesn’t always work. When a person’s depression persists after trying at least two different antidepressant drugs, it is called treatment-resistant depression.” – National Institutes of Health
- The STAR*D Study Findings: This massive study followed over 4,000 patients in everyday clinics. Only about a third of participants fully recovered after their first round of treatment, proving that even with identical medications, individual responses vary wildly.
Don’t put too much weight on the numbers, though. Studies use different patient groups, different clinic setti
ngs, and different definitions for what counts as ‘resistant.’ Statistics offer helpful context, but they cannot predict your individual recovery path or clinical outcomes.
Why Doesn’t Depression Always Respond to Treatment?
Depression treatment is rarely a one-size-fits-all process, and when medication or therapy doesn’t bring relief, it doesn’t mean your condition is untreatable. Often, what looks like a failed treatment is actually a sign that certain variables need adjusting or that an underlying factor was overlooked.
Before declaring a treatment ineffective, clinicians typically evaluate several key areas to ensure the current approach has been given a true chance to work.
Was the Treatment Given a Fair Chance?
Sometimes a medication appears ineffective simply because the conditions required for it to work weren’t fully met. Common reasons include:
- Insufficient duration: Stopping the medication before it has had enough time to build up in your system and take effect.
- Tolerability issues: Discontinuing use early because side effects were too uncomfortable to manage.
- Inconsistent dosing: Unintentionally missing doses frequently enough to disrupt the therapeutic effect.
- Sub-therapeutic dosage: Remaining on a dose that is too low to produce a noticeable clinical response.
These challenges are common and not a personal failure, but they can make a viable treatment look like a dead end.
Uncovering Hidden or Co-Occurring Factors
If medication adherence and dosage are solid, the next step is looking at what else might be influencing your recovery. Underlying factors can complicate treatment and require a modified approach:
- Co-occurring mental health conditions: High levels of anxiety, unresolved trauma, or PTSD can make depression far more complex to manage.
- Medical and lifestyle contributors: Chronic sleep problems, thyroid issues, vitamin deficiencies, or heavy alcohol and substance use can actively interfere with brain chemistry and medication efficacy.
- Interactions and stress: Unmanaged environmental stress or interactions with other daily medications can dampen treatment benefits.
When anxiety is heavily mixed with depressive symptoms, specialized options, such as targeted therapies, medication adjustments, or non-invasive neurostimulation like TMS therapy for anxious depression in Jacksonville, may be considered to address both components effectively.
Re-Evaluating the Diagnosis
When standard treatments consistently fail to help, doctors often revisit the original diagnosis to ensure the treatment plan targets the right root cause:
- Bipolar Disorder: Depressive episodes in bipolar disorder look identical to unipolar depression, but standard antidepressants can be ineffective or even counterproductive without mood stabilizers.
- Sleep Apnea & Physical Illness: Conditions that disrupt deep sleep or alter metabolic function frequently masquerade as major depression.
- Trauma: Symptoms driven by PTSD often require trauma-focused psychotherapy rather than reliance on medication alone.
Revisiting these possibilities isn’t about questioning your experience, it’s about gathering better information regarding your symptom history, physical health, and family background to ensure your next step is a smarter, more targeted one.
How Do Doctors Actually Diagnose It?

Diagnosing treatment-resistant depression (TRD) isn’t about running a lab test, there’s no blood work, brain scan, or definitive lab marker that gives a simple yes or no. Instead, doctors have to build a complete picture from your personal treatment history and symptom patterns.
Evaluating Your Treatment History
The core of the diagnosis comes down to a careful review of every antidepressant you’ve taken in the past. Your doctor will look at several specific factors:
- Medication details: Exactly which medications you tried, the doses you reached, and how many weeks or months you stayed on each one.
- Treatment duration: Whether you took the medication long enough, typically six to eight weeks at a maximum tolerated dose, for it to actually work.
- Reasons for stopping: Whether you discontinued due to severe side effects, a complete lack of response, or partial improvement that stalled out.
- Consistency: How regularly you were able to take the dose as prescribed.
The landmark STAR*D study highlighted why this patient history matters so much: in that trial, initial medication steps were evaluated over 12 to 14 weeks before declaring a treatment unsuccessful.
What a Full Diagnostic Evaluation Covers
During a comprehensive psychiatric evaluation, clinicians systematically map out your overall health and lifestyle to distinguish true treatment resistance from other underlying factors.
- Symptom Impact: How depression affects your sleep, work performance, personal relationships, and basic daily routine.
- Therapeutic History: Previous experience with psychotherapy (like CBT or DBT), electroconvulsive therapy (ECT), or interventional treatments.
- Co-Occurring Conditions: Underlying medical issues (like thyroid dysfunction) or co-occurring mental health conditions (such as anxiety, ADHD, or PTSD) that might mimic or worsen depression.
- Personal Goals: What recovery looks like to you, beyond just a slight reduction in symptoms.
This process helps your doctor separate partial improvement from full remission. Partial relief still leaves lingering symptoms that disrupt daily life and increase the chance of relapse.
Specialized Care and Interventional Options
When standard medications fail to deliver full relief, specialized clinics offer alternative pathways. For example, local practices like Fit Mind Therapeutics in Jacksonville evaluate patients for advanced options like NeuroStar Transcranial Magnetic Stimulation (TMS). Because therapies like TMS are prescription-only, a thorough diagnostic assessment ensures you meet the clinical criteria before starting treatment.
Preparing for Your Appointment
To get the most out of your evaluation, write down a simple chronological list of past medications, estimated doses, approximate dates, and why you stopped taking them. Having that timeline ready saves valuable time and helps your doctor map out an effective next step much faster.
What Treatments Are Available for Treatment Resistant Depression?
So the first antidepressant didn’t work. That happens more than people think. It doesn’t mean you’re stuck. Doctors have other paths. They can try a new medicine, add a second one on top, bring in therapy, or move toward something stronger like TMS, ECT, or esketamine.
A lot of what we know comes from one big study. It’s called STAR*D. Over 4,000 patients. Researchers followed them as they tried treatment after treatment, step by step.
Switching medicine means you drop one drug and try something else. Maybe it works differently. Maybe the side effects are gentler. Depends on the person.
Augmentation, or adding a new treatment to your existing medication, is another strategy. In the STAR*D study, about one in three people who augmented their treatment experienced significant improvement.
Therapy still counts too. CBT, for example, can stand on its own or work right alongside medication.
| Treatment Approach | What It Involves | Key Consideration |
| Switching medication | Replacing the current antidepressant with another medication. | May be considered when the current medication provides insufficient benefit or causes difficult side effects. |
| Augmentation | Adding another treatment while continuing the current antidepressant. | The choice depends on symptoms, previous response, side effects, and other health factors. |
| Psychotherapy | Using structured therapies such as cognitive behavioral therapy (CBT). | May be used alone or alongside medication. |
| TMS | Using magnetic stimulation to target specific areas of the brain. | May be considered for eligible patients who have not improved enough with standard treatments. |
| ECT | Using controlled electrical stimulation under medical supervision. | Often considered when depression is severe, persistent, or requires a faster response. |
| Esketamine | Using an FDA-cleared nasal spray alongside an oral antidepressant. | Requires administration and monitoring under an approved treatment program. |
Esketamine (brand name SPRAVATO) is an FDA-cleared nasal spray for adults with treatment-resistant depression. Here’s what you need to know:
- You take it along with your regular antidepressant pill, not instead of it.
- It’s only available at certified clinics. You can’t take it at home.
- You stay at the clinic for at least 2 hours after each dose so staff can monitor you.
- Side effects like drowsiness, dizziness, and dissociation are common but temporary.
The monitoring requirements aren’t optional, they’re in place to keep you safe.
How Is Esketamine Different From Ketamine?
Here’s the thing. Esketamine has FDA approval specifically for depression. Regular ketamine does not. It’s approved as an anesthetic. Doctors sometimes use it for depression anyway, but that use falls outside its official approval. Off label, as it’s called.
Esketamine only comes as a nasal spray. Only in a clinic. Ketamine gets used differently, and it’s really up to a doctor’s own judgment.
After a dose, you stay at the clinic. At least two hours. Staff keep checking on you the whole time.
And it’s a controlled substance too, which means there’s some risk of misuse built in. That’s a big part of why it’s so tightly managed.
What Should Patients Know About Safety?
You always take esketamine at a clinic under direct observation, where you will stay for a minimum of two hours afterward.
Post-Treatment Effects and Precautions
Feeling sleepy or spaced out after treatment is normal, and these effects usually wear off within a few hours. Because they can temporarily impair your coordination and judgment:
- Don’t drive or operate machinery for the rest of the day.
- Avoid making major decisions (financial, legal, etc.) for the rest of the day, or until you feel completely clear-headed and alert.
- Follow your clinic’s specific instructions about returning to normal activities.
Clinic Safety Protocol
- Your clinic team checks on you regularly during the 2-hour observation period to ensure you’re safe before leaving.
- Staff actively monitor for slowed breathing and other serious issues, which is precisely why the two-hour window matters so much.
How Well Do These Treatments Work?
Generally speaking, each time a treatment fails and you move to the next one, remission gets a bit harder to reach. That’s true across large groups of people though. Not a promise about what happens to you specifically.
| STAR*D Treatment Step | Approximate Remission Rate | What the Result Shows |
| Initial antidepressant treatment | About 1 in 3 | A substantial proportion of participants reached remission with the first treatment. |
| Second-step medication switch | About 25% | Some participants achieved remission after switching medications. |
| Second-step augmentation | About 1 in 3 | Augmentation helped some participants who had not remitted with the initial treatment. |
| Third-step treatment | About 12-20% | Remission remained possible, but rates were lower after additional treatment failures. |
| Fourth-step treatment | About 7-10% | Some participants still achieved remission after several previous treatment attempts. |
These numbers all come from STAR*D, published back in 2006. Everyone started on the same drug, citalopram, then branched out from there, switching or adding treatments. The study measured full remission. Not just feeling a bit better. That distinction matters if you’re trying to understand improving versus actually recovering.
STAR*D pulled in all kinds of patients too. Regular doctor’s offices, specialty mental health clinics, a broad mix. That makes it feel more real than a lot of smaller drug trials.
Still. It’s an older study. Newer treatments exist now that didn’t back then. What’s right for you comes down to your own story. Past medicines, other health conditions, side effects you’ve dealt with, what you’re actually comfortable trying.
What Should You Ask Before Starting Another Depression Treatment?

Navigating treatment-resistant depression requires a methodical approach, especially when previous options haven’t given you the relief you need. Before your next appointment, taking inventory of your treatment history and preparing targeted questions ensures you and your clinician make decisions based on clear evidence rather than guesswork.
What to Document Before Your Appointment
Before meeting with your doctor, write down a detailed log of your past treatments. This helps determine whether previous attempts received a true, fair trial.
- Medication History: List every antidepressant or adjunct medication you have taken, including the exact dosages and how many weeks or months you remained on each.
- Side Effect Profile: Note any physical or emotional side effects you experienced, paying close attention to quiet disruptions like insomnia, weight changes, or emotional blunting.
- Partial Responses: Record whether a medication improved your mood even slightly, as a partial response can signal that adjusting the dose or adding an augmenting agent might work better than switching entirely.
- Goals & Expectations: Outline what functional improvements matter most to you right now, whether that is returning to work, improving focus, or simply getting through the day.
Essential Questions for Your Doctor
About Your Treatment History
- Which medications or combinations have we not yet tried that target different neurotransmitter pathways?
- Looking back at my history, did I stay on previous medications at therapeutic doses long enough for them to fully work?
- Were there subtle side effects from past treatments that might have interfered with my daily life or adherence?
About Costs and Insurance
- Is this proposed treatment covered by my health insurance, and what will my out-of-pocket responsibility be?
- If cost is a barrier, reviewing how much TMS therapy costs can help you navigate insurance coverage, copays, and out-of-pocket expenses before committing.
- What happens if my insurance denies coverage, are there patient assistance programs or alternative options?
About Expectations and Progress
- Key Benchmarks: How will we objectively measure whether this treatment is working, and what specific symptom changes should I look for first?
- Timeframe: How many weeks should we stick with this new approach before deciding to adjust or change course?
- Next Steps: What is our backup plan if this option does not bring sufficient relief?
About the Clinician and Facility
- Provider Experience: How much experience do you have managing treatment-resistant depression with this specific modality?
- Patient Outcomes: What typical response or remission rates do you see in your practice for patients with a profile similar to mine?
- Care Coordination: How frequently will we schedule follow-ups to review progress and adjust the treatment plan?
Measuring Progress Objectively
Relying on memory alone makes it difficult to assess whether a treatment is working. Objective measurement tools remove the guesswork from your care.
- Symptom Tracking: Standardized clinical tools, such as the 9-question PHQ-9 depression scale, convert subjective feelings into concrete numerical data.
- Identifying Trends: Tracking scores over time reveals incremental progress that you might not feel day-to-day, like a score dropping from 18 to 12.
- Timely Adjustments: If your score remains static over several weeks, it provides clear, black-and-white evidence that it is time to adjust your dosage, add an augmenting strategy, or pivot to alternative therapies like TMS, ECT, or esketamine.
The newest or most aggressive option is not always the necessary next step. Often, finding the right path forward comes down to re-evaluating past trials, addressing overlooked side effects, or using consistent tracking to guide your care.
What specific treatment options, like a new medication, TMS, or therapy, are you hoping to discuss at your next appointment?
How Can Specialized Care Help With Depression That Has Not Responded to Treatment?
Specialized care shifts the approach from standard trial-and-error to a targeted, expert-led evaluation designed specifically for treatment-resistant depression. When standard options haven’t delivered results, a specialist looks beyond basic symptom management to re-evaluate the full picture and build an advanced strategy tailored to your exact history.
Comprehensive Psychiatric Evaluation
A specialist sits down with you, goes over your history, and helps you systematically think through what comes next. That means evaluating the medications and therapy you’ve already tried, your specific symptom profile, side effects, co-occurring health conditions, and your personal priorities. All of this guides your doctor in deciding whether to adjust your medication approach or move toward advanced interventions.
When you visit Fit Mind Therapeutics for an evaluation, clinicians conduct a comprehensive assessment. Based on this clinical review, providers may recommend Transcranial Magnetic Stimulation (TMS), targeted medication adjustments, or therapy. The clinical team clearly explains expectations without offering guaranteed outcomes:
- Medical & Psychiatric Review: A thorough review of your full diagnostic history, past treatment attempts, and underlying physical health.
- Physical & Lab Assessment: A physical examination and review of recent lab work to rule out biological contributors.
- Goal-Setting Discussion: A focused conversation about your personal treatment goals and what matters most to your quality of life.
- Financial & Insurance Planning: A clear review of your insurance coverage, out-of-pocket estimates, and overall treatment costs.
Evidence-Based Treatment Pathways
Based on this evaluation, I may recommend Transcranial Magnetic Stimulation (TMS), targeted medication adjustments, specialized therapy, or a combination approach. I will always clearly explain:
- Why I am recommending a specific treatment over other options
- What clinical evidence says about its effectiveness for your specific history
- What potential side effects and risks you should anticipate
- What the total cost will be and whether your insurance covers it
- How we will measure progress and when we should consider changing course
I cannot promise you will respond to a specific treatment. What I can promise is complete honesty, transparency, and an ongoing commitment to working with you until we find what works.
Core Components of a Focused Treatment Plan
- Historical Analysis: Reviewing what you have already tried to avoid repeating ineffective treatments.
- Broad Spectrum Care: Talking through both advanced medication and non-medication options like TMS.
- Continuous Monitoring: Keeping close track of your day-to-day symptoms and any emerging side effects.
- Progress Tracking: Checking how your brain and mood are responding over defined timeframes.
- Adaptive Strategy: Promptly changing course if the current plan is not yielding sufficient relief.
- Transparent Communication: Being completely candid about benefits, limits, and alternative routes.
Why Does an Individualized Plan Matter?
No single treatment works for everyone whose depression has not responded to earlier care. How you responded in the past directly dictates your next step, partial improvement points to a different strategy than a complete lack of response, and repeating medications that caused severe side effects rarely yields better results.
Your doctor will also evaluate your medical history, current medications, sleep patterns, anxiety levels, substance use, and potential signs of bipolar disorder. Research from NIMH shows that co-occurring anxiety significantly alters how antidepressants work, making a whole-picture assessment essential. Ultimately, an individualized plan is dynamic: as your symptoms, side effects, or personal goals shift, your treatment plan shifts right alongside them.
What Is the Outlook When Depression Has Not Responded to Treatment?

It’s understandable to feel exhausted and discouraged when depression hasn’t improved with initial treatments. However, a lack of early progress is not the end of the road; it signals a need for a more tailored, advanced approach. Treatment-resistant depression simply means the path forward requires a more tailored approach, close collaboration with your care team, and a broader look at available therapies.
Understanding Progress: Response vs. Remission
Medical professionals measure improvement using two key benchmarks:
- Response: Your symptoms decrease noticeably (typically by 50% or more). You experience meaningful relief and improved daily function, even if some symptoms linger.
- Remission: Your symptoms drop to a minimal level, allowing you to feel like yourself again and fully re-engage with daily life.
While full remission is always the ultimate goal, achieving a strong response is still a significant step forward that can help you return to work, rebuild relationships, and restore hope.
What the Evidence Shows
Findings from major clinical trials, such as the landmark STAR*D study, highlight how treatment outcomes evolve across multiple attempts:
- First Treatment: Roughly 1 in 3 people achieve full remission with their very first antidepressant medication.
- Second Attempt: For those who do not see full relief initially, about 1 in 4 reach remission after switching to a different medication or adding a second treatment.
- Subsequent Steps: While the statistical likelihood of complete remission decreases with each additional treatment step, people continue to find relief on their third, fourth, or fifth try.
Broad statistical averages describe populations, not individuals. Factors like your specific diagnosis, medical history, lifestyle, and adherence to therapy play a major role in shaping your unique recovery path.
Exploring Advanced Treatment Options
When standard first-line medications are not enough, healthcare providers often recommend alternative or combined approaches:
- Medication Strategies: Switching classes, optimizing dosages, or augmenting your current medication with mood stabilizers, atypical antipsychotics, or lithium.
- Psychotherapy Enhancements: Adding specialized talk therapies, such as Cognitive Behavioral Therapy (CBT) or Dialectical Behavior Therapy (DBT), to build coping mechanisms.
- Interventional Therapies: Considering advanced clinical procedures such as Transcranial Magnetic Stimulation (TMS), Spravato (esketamine), or Electroconvulsive Therapy (ECT).
- Lifestyle & Integrative Care: Addressing underlying medical conditions (like thyroid issues or sleep apnea) and incorporating structured exercise, nutrition, and stress management.
Taking the Next Step With Treatment-Resistant Depression
Living with treatment-resistant depression can leave you unsure what to try next, especially when previous treatments haven’t helped enough. You don’t have to assume that nothing will work. A structured review with a clinician can look at your treatment history, what helped, what didn’t, and which options may fit your needs.
The next step is getting a clearer plan based on your experience and goals. Fit Mind Therapeutics can help you discuss personalized treatment options, including approaches that may be considered when standard treatments haven’t provided enough relief.
If you are in immediate danger, feel unsafe, or are experiencing thoughts of suicide, call or text 988 (in the United States and Canada) to reach the Suicide & Crisis Lifeline, or go to the nearest emergency room.
FAQ
How Are Failed Antidepressant Trials Evaluated?
Failed antidepressant trials refer to previous medication courses that did not produce adequate symptom relief despite proper dosing and duration.
What Are the Official TRD Diagnosis Criteria?
Standard TRD diagnosis criteria require a lack of meaningful clinical improvement following at least two separate, adequate antidepressant trials.
What Are the Main TRD Treatment Options?
Available TRD treatment options include medication switches, augmentation therapy, psychotherapy, TMS, esketamine, and ECT.
How Does Augmentation Therapy for Depression Work?
Augmentation therapy for depression adds a secondary medication or therapeutic modality to an existing antidepressant to enhance its clinical effect.
What Does Partial Remission in Depression Mean?
Partial remission in depression indicates that symptoms have noticeably improved, though lingering issues continue to cause functional difficulty.
References
- https://www.mayoclinic.org/diseases-conditions/depression/in-depth/treatment-resistant-depression/art-20044324
- https://www.nih.gov/news-events/nih-research-matters/relieving-treatment-resistant-depression-older-adults